The Mental Game: Pain, Fear & Depression
Breaking the psychological cycle that keeps you in pain — how fear-avoidance, catastrophizing, and depression amplify back problems and what to do about it.
The mechanic's rule: Fear can protect an irritable back for a day and imprison it for a year. The way out is evidence gathered through tolerable action.
The Pain-Psychology Connection
Back pain is a real physical experience influenced by biological, psychological, and social factors in different proportions for different people. Psychological factors do not make pain imaginary, but fear, stress, mood, sleep, and expectations can influence symptom intensity, disability, and recovery behavior.
This isn't "the pain is in your head." The pain is real, physical, and has an identifiable mechanical cause. But your brain's interpretation of that pain — the fear, the catastrophizing, the hopelessness — directly amplifies the pain signal and can prevent recovery even when the tissues have healed.
No single percentage usefully divides a person's disability into "physical" and "psychological" parts. Assess the factors that are actually present: tissue sensitivity and neurological function, movement and load tolerance, sleep, fear, mood, work demands, and social support. Addressing the relevant combination is more useful than forcing every case into one category.
The Fear-Avoidance Cycle
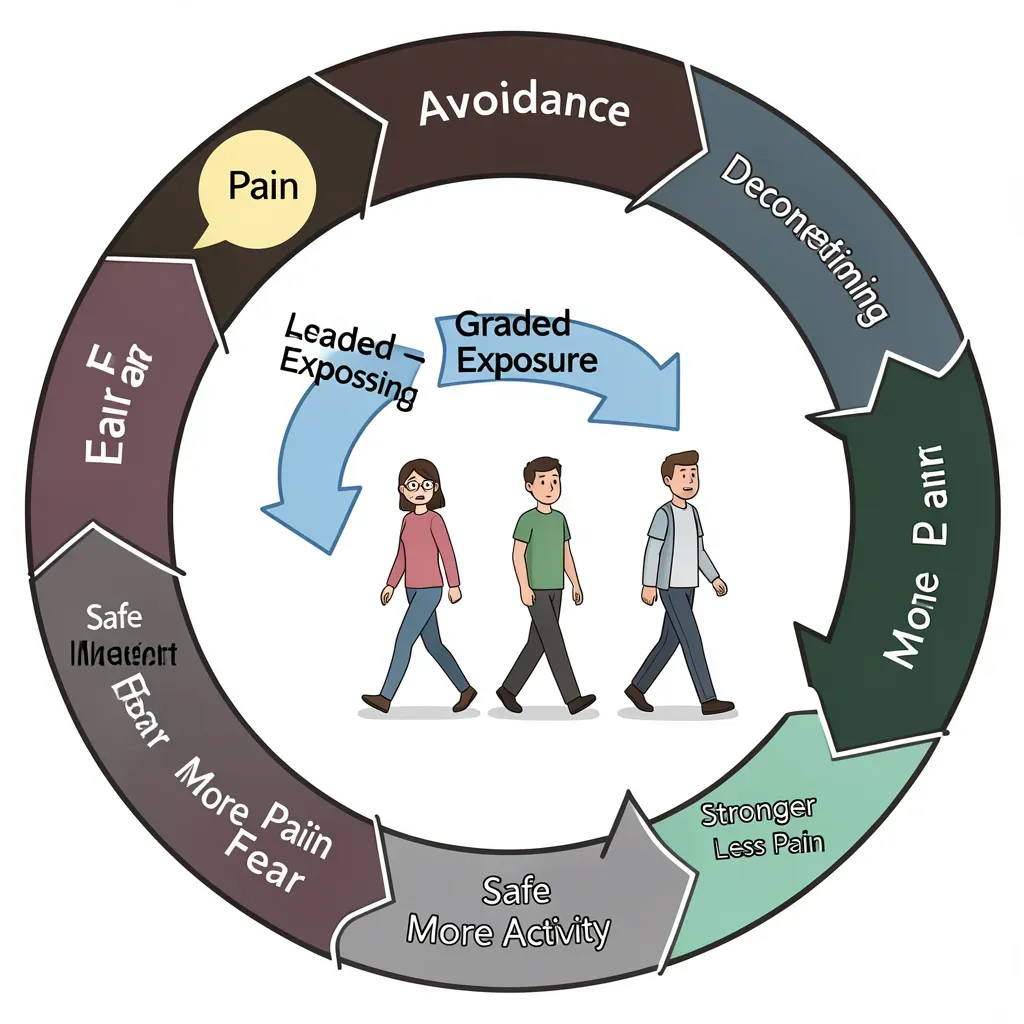
This is the most common psychological trap in chronic back pain:
- You experience pain during a movement (bending, lifting, walking)
- You develop fear of that movement ("bending will hurt me")
- You avoid the movement entirely (stop bending, stop walking, stop living)
- Muscles decondition and joints stiffen from disuse
- When you finally DO the movement, it hurts MORE (because you're weaker and stiffer)
- The fear is "confirmed" — you avoid even more
- Your world shrinks — depression follows
The cycle is self-reinforcing. Each loop makes the next one worse. And the tragic irony: the avoidance that feels protective is actually causing the very disability you're trying to prevent.
Breaking the Cycle
The solution isn't "just push through pain" — that causes tissue damage and reinforces the pain experience. The solution is graded exposure: carefully and progressively expanding your movement repertoire in a pain-free way.
This is exactly what the walking program and Big 3 do. They give you pain-free movement that PROVES to your nervous system that movement is safe. Each pain-free rep is a data point that rewrites the fear response.
Catastrophizing: The Pain Amplifier
Catastrophizing is the tendency to:
- Ruminate: "I can't stop thinking about how much this hurts"
- Magnify: "This is the worst pain imaginable, it must be something terrible"
- Feel helpless: "There's nothing I can do, it will never get better"
Research shows that catastrophizing is one of the STRONGEST predictors of chronic pain outcomes — stronger than the actual tissue damage visible on imaging.
Why It Amplifies Pain
Your brain has a "volume knob" for pain signals. When you catastrophize:
- Your nervous system becomes hyper-vigilant (scanning for threats constantly)
- Pain signals are amplified before they reach consciousness
- Muscles around the painful area tense up (guarding), increasing mechanical load
- Sleep quality drops, which can increase pain sensitivity and make recovery behaviors harder to sustain
- Inflammation increases through stress hormones
How to Turn Down the Volume
1. Understanding = power. Simply knowing that pain doesn't equal damage reduces catastrophizing. A disc bulge that you understand and can influence is far less frightening than mysterious "back problems."
2. Track your wins. Keep a log of pain-FREE activities. Most catastrophizers focus exclusively on what hurts. Force yourself to notice what DOESN'T hurt.
3. Challenge the absolutes. "My back is ruined" → "My back is currently sensitized but responding to treatment." "I'll never be active again" → "I walked 5 more minutes today than last week."
4. Take action. Catastrophizing thrives in passivity. Every time you perform a Big 3 exercise, complete a walk, or successfully use a movement tool, you're gathering evidence against the catastrophic narrative.
A tolerable movement can provide useful evidence against an “everything is destroyed” narrative. If you can walk five steps comfortably, that is a starting point to build from—not proof of a particular diagnosis or guaranteed outcome.
Depression and Chronic Pain
Depression and chronic pain share neural pathways. They are not separate problems — they feed each other in a bidirectional loop:
Pain → Depression:
- Chronic pain reduces activity → loss of enjoyable activities → isolation → depression
- Pain disrupts sleep → fatigue → hopelessness
- Pain limits work capacity → financial stress → depression
- Pain impairs concentration → reduced effectiveness → self-worth drops
Depression → Pain:
- Depression reduces motivation to exercise → deconditioning → more pain
- Depression amplifies pain perception (shared serotonin pathways)
- Depression disrupts sleep → inflammation → tissue sensitivity
- Depression creates muscle tension → increased spinal loading
- Depression reduces adherence to the recovery program
Recognizing the Signs
If you notice:
- Loss of interest in activities you previously enjoyed
- Persistent fatigue beyond what pain explains
- Sleep disruption (too much or too little)
- Feelings of worthlessness or excessive guilt
- Difficulty concentrating or making decisions
- Withdrawal from friends, family, social activities
- Thoughts that things will never improve
These indicate the depression side of the loop is active and needs direct attention.
Depression in chronic pain patients is NOT weakness. It's a predictable neurological response to sustained pain. Just as your muscles decondition without use, your mood regulation systems decondition under chronic pain. Both require active rehabilitation.
Practical Strategies for the Mind
1. The Activity-Mood Log
For one week, track:
- Every activity you perform
- Your pain level during and after (0-3)
- Your mood during and after (1-5 scale)
You'll likely discover:
- Some activities improve BOTH pain and mood (usually: walking, socializing, light exercise)
- Some activities worsen both (usually: prolonged sitting, isolation, dwelling on pain)
- The relationship between activity and mood is stronger than between activity and pain
Use this data to deliberately schedule more mood-boosting activities into your week.
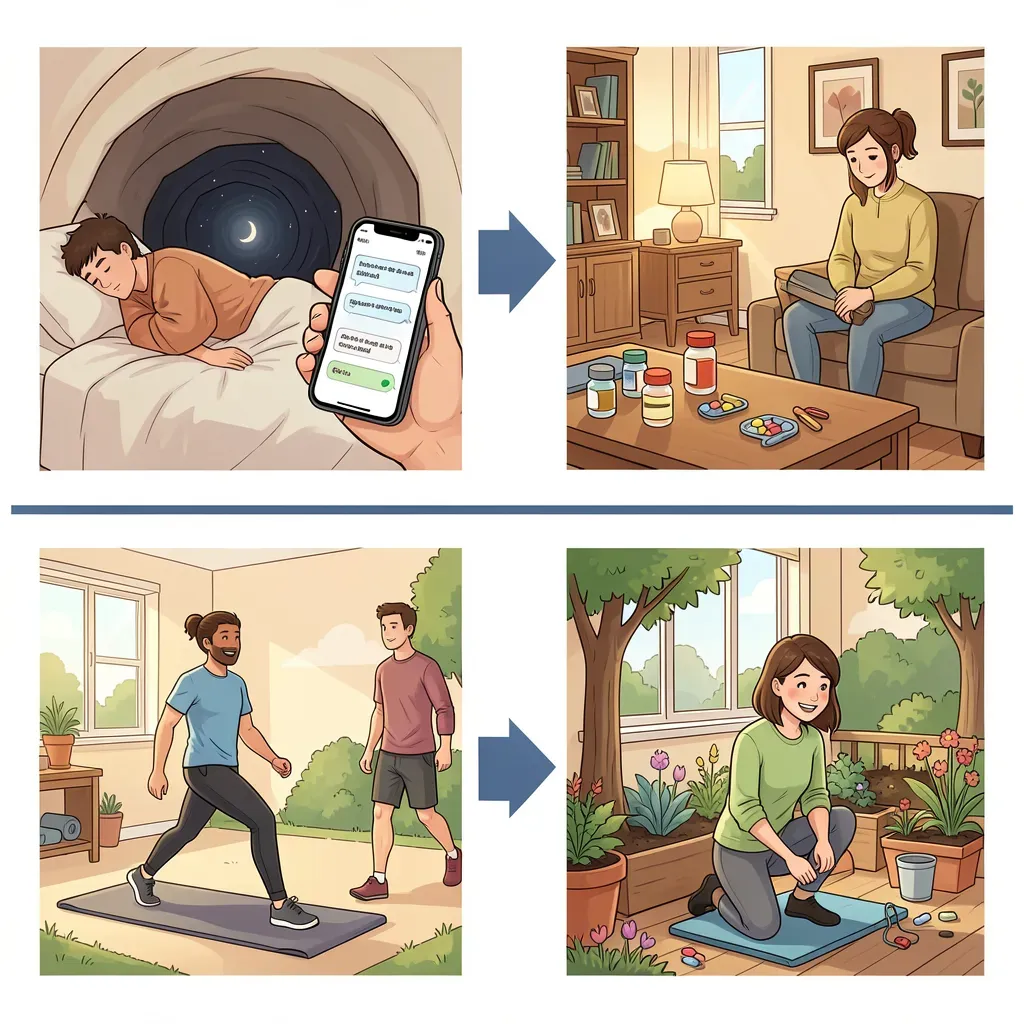
2. Sleep Hygiene for Pain
Poor sleep sensitizes the nervous system, amplifying pain the next day. Prioritize:
- Consistent sleep/wake times (even on weekends)
- Find your pain-free sleeping position (see the Special Conditions guide)
- No screens 60 minutes before bed
- Cool room temperature
- If pain wakes you: get up, find a relief posture, wait for it to pass, return to bed
- Don't "catastrophize in the dark" — get up, move, do something neutral
3. Social Connection
Isolation is both a symptom and accelerator of pain-related depression. Even when you don't feel like it:
- Maintain at least one social interaction per day (in person, phone, or video)
- Tell people what helps ("I need to stand after 30 minutes" is perfectly reasonable)
- Find a walking partner — accountability + social interaction + exercise in one activity
- Consider a support group (online or in-person) for chronic pain
4. Meaningful Activity
Pain often strips away the activities that give life meaning. The solution isn't to wait until pain is gone — it's to find modified ways to engage in meaningful activity NOW.
- Can't garden for 2 hours? → Garden for 15 minutes with proper spine hygiene
- Can't play 18 holes? → Chip and putt for 30 minutes
- Can't run? → Walk briskly with good technique
- Can't lift heavy? → Train movement patterns with light weight
Each modified activity serves double duty: it maintains your identity as an active person AND it builds physical capacity.
5. Redefine Success
If success = "no pain ever," you will feel like a failure every day. Redefine:
- Success = "I walked 10 minutes without triggering a flare"
- Success = "I got through a workday using spine hygiene"
- Success = "I identified my pain trigger and avoided it"
- Success = "I did my Big 3 despite not feeling motivated"
Small wins compound. A week of small wins changes your narrative from "I'm broken" to "I'm recovering."
When to Seek Professional Help
The strategies above are powerful but they have limits. Seek professional mental health support if:
- Depression persists beyond 2 weeks despite your best efforts
- You're unable to motivate yourself to follow the program at all
- You're having thoughts of self-harm
- Anxiety about movement is so severe you can't begin even the simplest exercises
- You're relying on opioids or alcohol to cope with pain
- Your relationships are deteriorating significantly
A psychologist specializing in chronic pain (or Cognitive Behavioral Therapy for pain) can provide structured support for breaking the cycle. This is NOT a sign of failure — it's using every tool available.
Research shows that the most effective treatment for chronic back pain combines physical rehabilitation (movement, exercise, spine hygiene) WITH psychological support (CBT, graded exposure, catastrophizing reduction). Neither alone is as effective as both together. You are allowed to need both.
A Mindset That Supports Recovery
People who recover from chronic back pain share these beliefs:
- "My pain has a physical cause that I can identify and influence"
- "Movement is medicine — I will find ways to move safely"
- "Bad days don't erase good days — the trend matters, not any single day"
- "I am an active participant in my recovery, not a passive patient"
- "Change is possible, and I can judge progress by what I am gradually able to do"
These statements are not a promise of recovery. They are more accurate and useful alternatives to absolute predictions, and they support the small, repeatable actions through which function can improve.
The Mechanic's Brief
- Pain is real whether its dominant drivers are tissue sensitivity, nervous-system sensitivity, context, or a combination.
- Fear and catastrophizing can reduce useful activity, but dismissing pain as imaginary is equally unhelpful.
- Use graded, successful experiences to rebuild confidence in a valued movement.
- Seek professional mental-health support when mood, sleep, anxiety, or safety concerns interfere with recovery.